Skip to content

How to Choose a Patient Monitoring System?

Choosing a patient monitoring system is not a shopping exercise. It is a clinical decision with consequences at the bedside. The right system should help staff notice meaningful changes, respond promptly, and avoid drowning in alarms. A bright screen alone proves little.

Patient-safety pioneer Dr. Lucian Leape warned, “The single greatest impediment to error prevention in the medical industry is that we punish people for making mistakes.” His point matters here: reliable monitoring depends on people and processes, not devices alone. A useful evaluation should examine patient acuity, care settings, sensor comfort, alarm controls, and how clearly trends appear during a busy shift. Can nurses find the information they need without extra clicks? Can the system connect safely with existing records and devices? Small workflow details count.

Look beyond the feature list. Ask how the system performs during movement, weak connectivity, and routine cleaning. Check evidence for the intended patient population, staff training, technical support, cybersecurity practices, and total ownership costs. Request a realistic demonstration, not just polished slides. Watch a clinician silence an alarm, review a trend, and hand off care. Then ask what could still go wrong. There will be gaps; no system removes clinical judgment or guarantees better outcomes. A careful choice matches validated capabilities to local needs, with clear plans for testing, maintenance, and review after deployment.

How to Choose a Patient Monitoring System?

Define the Clinical Needs and Monitoring Goals

Choosing a patient monitoring system starts with the people and clinical decisions it must support. Define the patient groups, care settings, and risks before comparing devices. A post-operative patient may need continuous oxygen saturation and heart-rate monitoring, while a stable patient on a general ward may need scheduled observations. That matters. Consider age, mobility, skin sensitivity, and whether patients can move between rooms without losing reliable readings.

List the measurements clinicians need, such as heart rate, blood pressure, oxygen saturation, temperature, or respiratory rate. Set goals that can be observed: earlier recognition of deterioration, fewer missed observations, or clearer escalation to the right clinician. A threshold should reflect local clinical protocols and patient context, not a convenient default. Small details count. Assess how alarms reach staff, whether they distinguish urgent changes from routine alerts, and how readings fit into existing workflows. An alarm that sounds often but prompts no clear action can add noise rather than useful information. A plan can look tidy on paper and still fail during a busy night shift. Review likely staffing, connectivity, cleaning, and training needs with frontline clinicians. Then test the proposed workflow using realistic scenarios, including a patient who is asleep, moving, or temporarily away from the bedside.

Identify the Patient Population and Care Environment

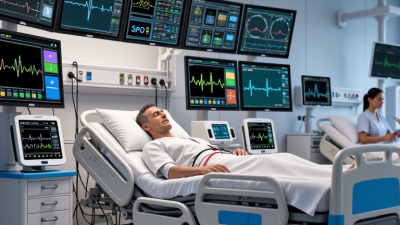
Choosing a patient monitoring system starts with the people it must serve, not the feature list. A neonatal unit needs sensors sized for small bodies and alarms tuned to rapid physiological changes. A step-down ward may prioritize continuous ECG, oxygen saturation, and mobility-friendly wearables. For older adults, fragile skin, hearing loss, and frequent movement can affect comfort and signal quality. The World Health Organization’s 2022 ageing report projects that the global population aged 60 and older will reach 1.4 billion by 2030. That shift makes usability and clear trend displays increasingly important. Age alone is a poor shortcut.

Then examine the care environment. In an ICU, staff may need central visibility across beds and reliable alarm routing. On a general ward, battery life, wireless coverage, and easy cleaning can matter more during routine rounds. Home monitoring brings different constraints: patients may live alone, have limited internet access, or need simple instructions. The 2023 National Healthcare Quality and Disparities Report from AHRQ documents persistent differences in healthcare access and quality across populations. Those differences should inform device selection, not just procurement. Test sensors on representative patients, check connectivity in real rooms, and ask nurses what interrupts care. A polished demo can hide weak signals behind a closed door. It happens. Reassess the patient mix and workflow after deployment; the original assumptions may not hold.

Compare Monitoring Parameters and System Types

Compare Monitoring Parameters and System Types

Choose parameters around the clinical question, not the longest feature list. ECG tracks rhythm; pulse oximetry estimates oxygen saturation; blood pressure shows circulation trends. Add capnography when ventilation needs close observation, such as during sedation. WHO’s 2023 cardiovascular disease report estimates that 20.5 million people died from cardiovascular diseases in 2021. That burden makes reliable cardiac monitoring important, but it does not mean every patient needs continuous ECG. Match the measurements to acuity, mobility, and the decisions clinicians must make.

System type shapes what staff can see and how quickly they can respond. Bedside monitors suit close observation in critical care. Telemetry supports mobile patients who still need continuous ECG. Wearable and remote systems can collect readings beyond the ward, but connectivity gaps and delayed alerts need a plan. ECRI’s 2024 Top 10 Health Technology Hazards report highlights risks from inadequate alarm configuration. More alarms are not always safer.

Check sensor comfort, battery life, signal quality, and how trends appear at the central station. During a trial, walk the corridors and test realistic movement; a clean reading in a quiet room proves little. Review who receives each alert and what happens when a signal drops. I would also question whether every parameter is actionable. That part is easy to overlook.

How to Choose a Patient Monitoring System?

Compare the parameters commonly supported by bedside, transport, and wireless telemetry systems.

This is a general capability comparison, not a guarantee of included features. Availability depends on the monitor model, configuration, accessories, and patient type. Confirm required parameters, alarms, connectivity, and mobility needs before selecting a system.

Assess Usability, Connectivity, and Safety Features

Choose a patient monitor by watching how people use it under pressure, not by judging its display in a quiet showroom. Can a nurse wearing gloves silence a noncritical alert without hiding a dangerous one? Are heart rate, oxygen saturation, and trends readable from the doorway? A screen can seem obvious in a demonstration and still confuse a tired clinician at 3 a.m. Test routine tasks during realistic shifts. A small hesitation matters. Ask staff to adjust alarm limits, clean the device, and find a patient’s recent readings without coaching.

Connectivity deserves the same practical test. Confirm that readings reach the intended record, timestamps stay aligned, and connection failures are visible rather than silent. Check how the monitor behaves during Wi-Fi loss, patient transfers, and power changes. The AAMI Foundation’s 2011 alarm-summit report cited studies in which 85–99% of alarms were nonactionable; rates vary by setting. This makes configurable thresholds and clear alarm priorities important, not cosmetic. The Joint Commission’s 2013 Sentinel Event data summary recorded 98 alarm-related events from January 2009 through June 2012, including 80 deaths. Review alarm logs, escalation paths, and backup procedures with frontline staff. I would still question any system that works only when every connection behaves perfectly.

Evaluate Costs, Compliance, and Ongoing Support

How to Choose a Patient Monitoring System?
Evaluate Costs, Compliance, and Ongoing Support

A monitoring system’s price is only the beginning. Compare device, software, installation, network upgrades, staff training, and replacement costs over several years. Ask for a written breakdown of recurring fees and what happens when a sensor fails during a night shift. A low quote can hide expensive integration work. The IBM and Ponemon Institute 2024 Cost of a Data Breach Report put the average healthcare breach cost at $9.77 million. That is not theoretical. Include security controls, audit logs, access permissions, and patching in your cost assessment, not as optional extras.

Compliance requirements vary by location and care setting, so check how the system handles patient data, retention, access, and incident records. Ask the supplier to document its security practices and provide evidence for your organization’s review. Do not assume a checkbox proves compliance. It does not.

Support matters. Confirm response times, after-hours coverage, replacement-device availability, software update schedules, and who troubleshoots connection failures. Request a sample service agreement, then test its promises against a realistic outage scenario. Can staff keep monitoring safely while a device is replaced? A spreadsheet may still miss the human part: rushed training, unclear escalation, or one confusing alert. Build time for hands-on testing with the people who will use the system every day.

How to Choose a Patient Monitoring System? - Evaluate Costs, Compliance, and Ongoing Support
Evaluation Dimension What to Evaluate Evidence to Request Cost Considerations Practical Decision Check
Clinical fit and intended use Confirm the system supports the patient population, care setting, measured parameters, and monitoring workflow required by the organization. Intended-use statement, supported-patient specifications, clinical workflow demonstration, and limitations for use. A mismatch may lead to extra devices, workarounds, retraining, or replacement costs. Can clinicians use the system for the intended patients and care environment without relying on unsupported features?
Purchase and deployment costs Compare device or license charges, accessories, installation, configuration, network work, integration, and staff training. Itemized quotation, implementation plan, included services, and a clear list of optional charges. Initial purchase price is only one part of total cost; implementation and integration can add substantial project expense. Does the proposal show one-time and recurring costs separately?
Ongoing and lifecycle costs Assess subscription fees, service contracts, replacement sensors, consumables, software updates, battery replacement, and equipment refresh needs. Multi-year cost schedule, service-contract terms, consumable pricing, warranty details, and end-of-support policy. Recurring charges and replacement parts affect total cost of ownership over the system’s useful life. Can the organization estimate costs beyond the first year, including likely replacements and upgrades?
Regulatory status and intended market Verify the device’s regulatory status for the country where it will be used and whether that status matches its intended use. Applicable authorization or conformity documentation. In the United States, confirm the relevant FDA pathway; in the European Union, confirm applicable MDR requirements. Confirm whether documentation, configuration, or service requirements create additional implementation costs. Are the supplied documents relevant to the exact model, software version, intended use, and market?
Privacy and data protection Review what patient data is collected, where it is stored, who can access it, how long it is retained, and how it is deleted or exported. Data-flow diagram, access-control details, retention and deletion terms, incident process, and applicable contract terms. Security reviews, privacy assessments, data migration, and required integrations may require staff or vendor resources. For U.S. organizations subject to HIPAA, determine each party’s role and required safeguards; HIPAA compliance is not a generic product certification.
Cybersecurity and updates Assess authentication, encryption, user permissions, security logging, vulnerability handling, update processes, and the supported software lifecycle. Security documentation, update and patch policy, vulnerability disclosure process, and a defined security-support period. Network changes, security testing, and ongoing IT administration can add internal operating costs. Who applies updates, how are they tested, and how are urgent vulnerabilities communicated and addressed?
Interoperability and integration Check compatibility with the organization’s electronic health record, identity management, alarms, networks, and reporting workflows. Interface specifications, supported data formats or standards, integration responsibilities, and results from a workflow test. Interfaces, middleware, testing, and maintenance may involve separate costs. Are data transfers and alarms tested end to end in the intended clinical environment?
Alarm management and usability Evaluate alarm configuration, prioritization, escalation, visibility, workflow fit, and the steps needed to acknowledge or respond to alerts. Clinical demonstration, alarm configuration options, training materials, and a documented plan for local alarm review. Training and workflow redesign may be needed to support safe and effective use. Can clinical teams configure alarms appropriately and understand escalation responsibilities?
Technical support and service levels Review support hours, contact channels, response targets, escalation routes, remote-support controls, and repair or replacement arrangements. Written service-level terms, support coverage calendar, escalation process, and service-performance reporting approach. Higher service coverage may cost more but can reduce the impact of outages and delays. Do response and repair commitments match the criticality and operating hours of the care setting?
Training, maintenance, and continuity Confirm user and administrator training, preventive maintenance, device cleaning guidance, downtime procedures, and backup plans. Training schedule, maintenance instructions, cleaning guidance, troubleshooting materials, and continuity or downtime procedures. Refresher training, maintenance labor, spare equipment, and downtime planning should be included in the operating budget. Can the organization keep the system operational when a device, connection, or service is unavailable?

Note: Costs and regulatory requirements vary by system configuration, intended use, organization, and country. Verify current requirements and obtain itemized quotations before purchasing.